
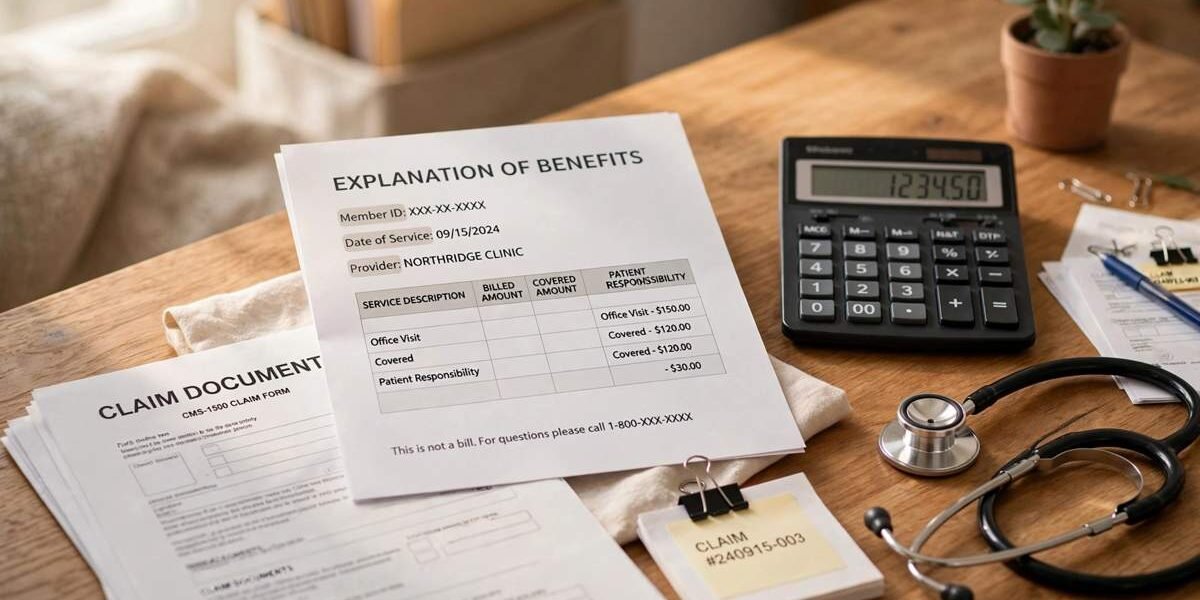
Quick answer: How to read an explanation of benefits? Start by remembering that an EOB is not a bill. It is a statement from your health plan explaining how it processed a claim: what service was reported, what the provider charged, what amount the plan allowed, what the plan paid, and what share, if any, is left as your responsibility. If you owe anything, the provider will send a separate bill for that amount, and that bill should match the patient-responsibility figure on the EOB.
What an EOB is, and when you get one
After you receive care, the provider sends a claim to your health plan. The plan reviews and adjudicates that claim, then sends you an EOB, usually by post or through your online member portal. It is the plan’s account of its decision, not a request for payment.
A few points that prevent most confusion:
- One claim can produce several EOB lines. Each service on the claim gets its own line, with its own date, description and amounts.
- A provider you do not recognise is not always an error. A radiologist, anaesthetist, laboratory or other clinician involved in your care may bill separately from the clinician you saw face to face. Check the date and service first before assuming a mistake.
- Original Medicare works slightly differently. People on Original Medicare receive a Medicare Summary Notice instead of a commercial-plan EOB. It plays the same role: it summarises what was billed, what Medicare approved and paid, and what you may owe.
- The provider gets its own version too. The provider’s statement of the same decision is called a remittance advice. The figures should agree with your EOB, even though the two documents look different.
EOB vs bill: the difference that matters most
| Document | Sent by | What it means |
| Explanation of Benefits (EOB) | Your health plan | How the claim was processed, and what your share is. This is not a bill. |
| Provider bill or patient statement | Your provider or facility | A request for payment of the amount left after insurance. This is the document to pay, after checking it against the EOB. |
The practical rule is simple: do not pay from the EOB alone, and do not pay a provider bill that is higher than the EOB’s patient-responsibility figure without asking why. A higher bill usually means an error, a duplicate line, a service still being corrected, or a charge for something the plan did not cover, each of which needs a different response.
Step 1: check the header before you read the money
Before the amounts, confirm the EOB is about the right person and the right visit:
- Patient name and member ID, is this your claim, or another family member’s?
- Provider or facility name, does it match where you received care?
- Date or dates of service, do they match your visit, test or procedure?
- Claim number, note this down. You will need it for any call, correction or appeal.
If the header is wrong, the rest of the EOB may belong to someone else’s claim. Contact the plan first, before acting on any figure in it.
Step 2: read each service line
Each line normally shows a service description, a procedure code, usually a CPT code for a clinician’s service, and the date it was performed. The description is your best clue for recognising the service: an office visit, a laboratory test, imaging, or a procedure.
If a line describes a service you did not receive, or the same service appears twice for the same date, do not pay it yet. Note the line, the date and the code, and raise it with the provider’s billing office first, duplicate and wrong-service lines are common billing errors, and they are usually corrected from the provider’s side.
Step 3: understand the four money columns
Most EOBs use the same four ideas, even when the column headings differ slightly by plan:
- Amount billed (charges): what the provider charged for the service. Think of this as the list price, before any plan discount.
- Allowed amount (approved amount): the most the plan recognises for that service under its contract or fee schedule, for an in-network provider. This is the figure everything else is calculated from, not the billed amount.
- Adjustment (discount or contractual write-off): the difference between billed and allowed, for an in-network service. The provider has agreed to accept the allowed amount, so this difference is written off and is not your responsibility.
- Plan paid (benefit paid): what the plan actually sent to the provider.
- Patient responsibility (amount you may owe): your share of the allowed amount. It is made up of some combination of deductible, copay, coinsurance and any non-covered charge. This is the only figure a provider bill should ask you for.
In short: billed minus adjustment equals allowed, and allowed minus plan paid equals your share (before any non-covered amount is added).
A worked example, with round numbers
This is an illustrative example only, with the deductible already met and a 20% coinsurance:
| Column | Amount |
| Amount billed | $500 |
| Allowed amount | $350 |
| Adjustment (billed minus allowed) | $150, written off, you do not pay this |
| Plan paid (80% of allowed) | $280 |
| Patient responsibility (20% coinsurance) | $70 |
So the provider bill for this service should be $70, not $500 and not $350. The $150 adjustment disappears because the provider agreed to the $350 rate. If you had not yet met your deductible, the split would look different: more of the allowed amount would fall to you first, and the plan-paid figure would be lower, possibly $0 for that line, without the claim necessarily being denied.
Deductible, copay and coinsurance, in plain language
These three terms make up most patient-responsibility figures:
- Deductible: the amount you pay out of pocket, from allowed amounts, before the plan starts sharing costs for most services. Deductibles usually reset each plan year.
- Copay: a fixed dollar amount for a particular service, such as a set amount for a primary-care visit, regardless of the service’s total cost.
- Coinsurance: your percentage share of the allowed amount after the deductible, commonly 20% for in-network care. It is a percentage, not a fixed fee, so it rises and falls with the allowed amount.
Many EOBs also show your progress toward your annual deductible and out-of-pocket maximum. Once you reach the out-of-pocket maximum for covered, in-network services, the plan generally pays the rest for the year, which is why tracking these totals across EOBs is worth doing.
Remark and adjustment codes: what CO and PR mean
EOBs explain adjustments with short codes, usually in a notes or remarks section. Two prefixes cover most lines:
- CO (contractual obligation): an adjustment the provider absorbs under its contract, such as the write-off between billed and allowed amounts. A common example is CO-45, for charges above the fee schedule. You should not be billed for a CO adjustment.
- PR (patient responsibility): an amount that falls to you, such as PR-1 for a deductible amount, PR-2 for coinsurance, or PR-3 for a copay.
Other codes explain why a line was reduced or denied, for example a missing piece of information or a service already adjudicated on an earlier claim. If a code is unclear, the notes section, or a call to the plan, asking for a plain-language explanation, is the next step. Quote the claim number and the line’s date and service, and note the name, date and reference number of the call.
What a $0 paid, denied or “not covered” line means
Not every $0 is a denial, and not every denial is final:
- $0 paid because of the deductible: the allowed amount was applied to your deductible. This is normal early in a plan year, and the line is not denied, it is simply your share for now.
- Denied line: the plan reviewed the line and decided not to pay it, for a stated reason, such as a coding mismatch, missing authorisation, or a service the plan does not cover. The reason code on the EOB is the starting point for a correction or appeal.
- Not covered: the service is not a benefit under your plan, or not covered in that setting or for that diagnosis. You may be responsible for the amount, but check first whether an exception, an alternative covered service, or a corrected code supported by the notes applies.
- Pending or corrected claim: a later EOB may replace an earlier one. If a corrected claim is being processed, wait for the new EOB before paying a bill based on the old one.
The full denial reasons and appeal steps are covered in the denials guide, start there with the EOB’s reason code in hand, rather than paying a denied charge immediately.
Check the EOB against the bill, line by line
When the provider bill arrives, compare it with the EOB before paying:
- Does the provider name and date of service match?
- Does each billed service match an EOB line, with no extra or duplicate lines?
- Does the total you are asked to pay equal the EOB’s patient-responsibility total?
- Are any CO adjustments, amounts the provider wrote off, missing from the bill, or wrongly added back?
- Is any line on the bill for a service the EOB shows as pending, denied or corrected?
If anything does not match, call the provider’s billing office with the EOB in hand, and call the plan if the two sides disagree. Do not pay the disputed part until the mismatch is explained; paying first and disputing later is much harder to unwind.
What to do if you spot an error
- Circle the line. Note the date, service, code, claim number and the figure that looks wrong.
- Call the provider’s billing office first for wrong services, duplicates and bill and EOB mismatches, these are usually provider-side corrections.
- Call the plan for coverage, allowed-amount and denial-reason questions, and ask for the explanation in plain language.
- Keep every EOB. They are the record of what was allowed, paid and applied to your deductible and out-of-pocket maximum. If a later bill or corrected claim arrives, the earlier EOB is what lets you spot the change.
- Watch the deadlines. Corrections and appeals have time limits, usually counted from the date on the EOB or denial notice, so do not leave a disputed line unqueried.
Frequently asked questions
Do I have to pay the amount shown on my EOB?
No, not from the EOB itself. The EOB is information, not a bill. Wait for the provider’s bill, check that it matches the EOB’s patient-responsibility figure, and pay the provider, not the plan, for that amount.
Why is the amount I owe lower than the amount billed?
Because the plan and the provider agreed on an allowed amount that is lower than the billed amount, and the difference is written off as a contractual adjustment. You pay only your share of the allowed amount.
Why did my plan pay $0 on a line?
Most often because the allowed amount was applied to your deductible, which had not yet been met. That is not the same as a denial. Check the remark code: if it points to a deductible, the line was processed normally; if it points to a denial reason, follow the appeal steps in the denials guide.
Why does my EOB show a provider I never saw?
It may be a clinician who was involved in your care behind the scenes, such as a radiologist, pathologist or anaesthetist. Check the date and service description first. If neither matches anything you received, raise it as a possible error.
What if I never received an EOB?
Check your plan’s online portal first, many plans now issue EOBs electronically and may not post a paper copy. If there is still no EOB, the claim may still be pending, or the provider may not have submitted it yet. Ask the provider for the claim submission date, then check the portal again.
How long should I keep EOBs?
Keep them at least until the provider bill is paid and matches, and ideally until the end of the plan year, so you can track your deductible and out-of-pocket totals and answer any corrected-claim or tax question from the same record.
Sources
- HealthCare.gov, glossary and health insurance terms, including allowed amount, deductible, copay and coinsurance
- HealthCare.gov, appealing a health plan decision
- Centers for Medicare & Medicaid Services, Medicare Summary Notice information, for the Original Medicare equivalent of an EOB

Cura Editorial Team
Contributor at Cura Health Journal.